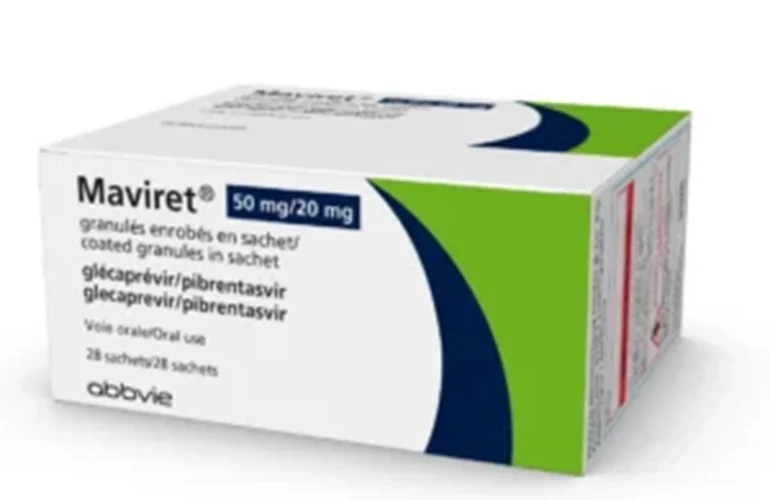
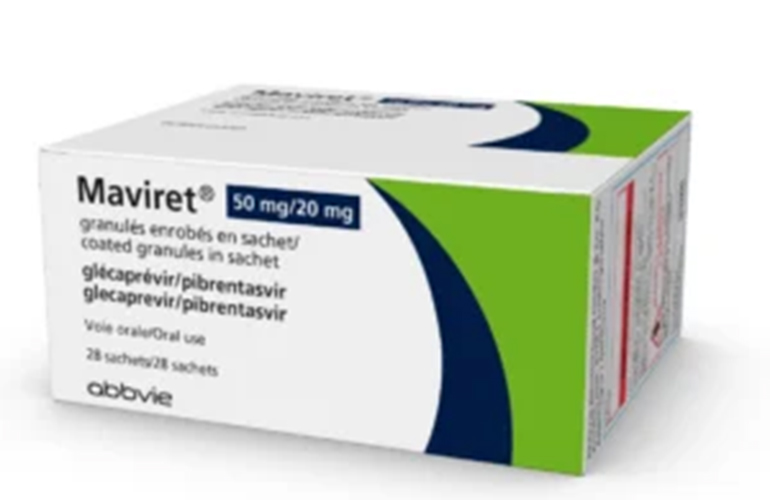
The landscape of hepatitis C (HCV) management has undergone a radical transformation over the last decade, yet the public health challenge posed by the virus remains paradoxically acute. In 2023, approximately 69,000 Americans contracted the virus—a figure roughly double the incidence rate recorded in the mid-2010s. This resurgence persists despite the availability of highly effective, direct-acting antiviral (DAA) therapies that have rendered the disease curable in as little as eight to 12 weeks. With the recent regulatory expansion for AbbVie’s Maviret (glecaprevir/pibrentasvir) to treat acute HCV infections in both the United States and the European Union, the medical community is now shifting its focus from simple drug efficacy to the complex logistical and social barriers that prevent these life-saving treatments from reaching the most vulnerable populations.
A Chronology of Treatment Evolution
To understand the significance of the latest approvals, one must look at the historical trajectory of HCV therapeutics. In 1991, the FDA granted approval for the first interferon-based therapies. These treatments were notoriously grueling for patients, often involving debilitating side effects, and achieved a viral eradication rate of only approximately 10%.
The paradigm shifted significantly in 2017 when the European Union and the U.S. Food and Drug Administration (FDA) approved Maviret for the treatment of chronic HCV across all major genotypes (1–6). This marked a transition to highly tolerable oral regimens. However, until recently, clinicians were often forced to wait for patients to transition from acute to chronic infection before initiating treatment, due to restrictive labeling.
The clinical landscape reached a new milestone in June 2025, when the FDA expanded the indication for Maviret to include acute hepatitis C, making it the first and only treatment specifically cleared for this stage of the infection. The European Commission followed suit in June 2026, granting a similar label expansion for the drug, marketed as MAVIRET in the EU. This regulatory shift was designed to eliminate the "watch-and-wait" approach, allowing for immediate intervention.
Clinical Efficacy and the Reality of Reinfection
The efficacy of Maviret is well-documented, with the recent Phase 3 clinical trial demonstrating a 96.2% sustained virologic response (SVR) at 12 weeks in the intention-to-treat population. In the modified intention-to-treat population—which excluded non-virologic failures—the cure rate reached 100%. Perhaps most notably, there were zero instances of on-treatment virologic failures or post-treatment relapses.
These figures are particularly salient given the demographics of the trial participants. Approximately 18% of the study cohort were individuals being treated for at least their second HCV infection, and nearly 40% of those had a history of two or more prior infections. Some participants had been treated as many as six times previously.
The trial results suggest that prior exposure to Maviret does not confer resistance or diminish the efficacy of subsequent treatment. "The study found that a history of prior HCV infection did not appear to affect the SVR," noted Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and a co-author of the study. "Moreover, no virologic failures were observed in the study, including among participants who had previously received Maviret for an earlier infection."
The Public Health Implications of "Hard-to-Reach" Populations
While the clinical data is robust, experts argue that the trial environment—highly controlled and monitored—does not fully reflect the complexities of real-world application. A critical concern is the reach of these therapies among populations least engaged in the formal healthcare system.
The Phase 3 trial was characterized by high retention rates, yet only 14.3% of participants were individuals who currently or recently injected drugs—a group that faces a significantly higher risk of reinfection. Furthermore, nearly half of the trial participants were co-infected with HIV but were already stabilized on antiretroviral therapy, meaning they were already integrated into a clinical care infrastructure.
For populations that are not regularly connected to healthcare, the "real-world" effectiveness of these drugs may be lower than the "clinical" efficacy. Reinfection rates among people who inject drugs are estimated at 5.9 per 100 person-years, significantly higher than the 1.27 per 100 person-years observed in the general population.
Dr. John Ward, director of the Coalition for Global Hepatitis Elimination, emphasizes that clinical success is only one half of the equation. "If treated early with safe and effective therapies, providers can cure virtually all patients with hepatitis C before it escalates to chronic disease," Ward noted. However, he acknowledges that the medical community must bridge the gap between drug availability and actual patient uptake.
Integrating Treatment with Harm Reduction
The consensus among infectious disease experts is that antiviral treatment cannot exist in a vacuum. Because the underlying behavioral and environmental exposures—such as substance use or lack of access to sterile equipment—remain unchanged by the medication, medical professionals argue for a holistic approach to HCV management.
"Antiviral treatment does not modify the underlying exposure," Dr. Gentile explained. "Repeated treatment must therefore be integrated into a broader prevention strategy, including harm-reduction services, access to sterile injecting equipment, treatment for substance-use disorders when appropriate, sexual-health interventions, regular HCV RNA testing, and rapid retreatment following reinfection."
This perspective redefines how clinicians should view patients with repeated infections. Rather than viewing reinfection as a failure of the therapy or a behavioral deficit in the patient, it is increasingly being treated as a signal that the patient requires more intensive support, linkage to social services, and expedited re-administration of medication. By viewing these individuals as high-priority candidates for elimination efforts, the public health sector can maximize the individual and societal benefits of the drug.
Future Directions and Administrative Barriers
The path forward involves dismantling the administrative and systemic barriers that contribute to patients disengaging from care. Before the recent acute-infection label expansion, clinicians often faced insurance denials or bureaucratic hurdles while waiting for confirmation of chronic infection. The new regulatory approvals are expected to streamline this process, allowing for "test-and-treat" models that are essential for mobile or marginalized populations.
Future research initiatives are now being designed to measure effectiveness beyond simple SVR. These studies aim to track metrics such as the time elapsed from initial diagnosis to the administration of the first dose, the proportion of diagnosed individuals who successfully complete the full course of treatment, and the effectiveness of rapid retreatment protocols.
The challenge for the next decade will be to translate the 96% clinical success rate into a public health victory. As AbbVie and other manufacturers continue to refine their delivery models, the focus must remain on creating a "low-threshold" care environment. This involves co-locating HCV testing and treatment within needle exchange programs, homeless shelters, and community health centers, rather than requiring patients to navigate traditional, often intimidating, hospital settings.
Ultimately, the availability of a highly effective cure for acute HCV is a triumph of pharmaceutical innovation. However, as the medical community has learned from decades of infectious disease management, a drug is only as effective as the system that delivers it. The success of Maviret will not be measured by its performance in a clinical trial, but by its ability to reach those who have been historically left behind, thereby curbing the current, concerning rise in new infections. By integrating pharmaceutical progress with robust, patient-centered prevention strategies, the medical community remains hopeful that the goal of global hepatitis C elimination is still within reach, provided the focus shifts from the laboratory to the community.