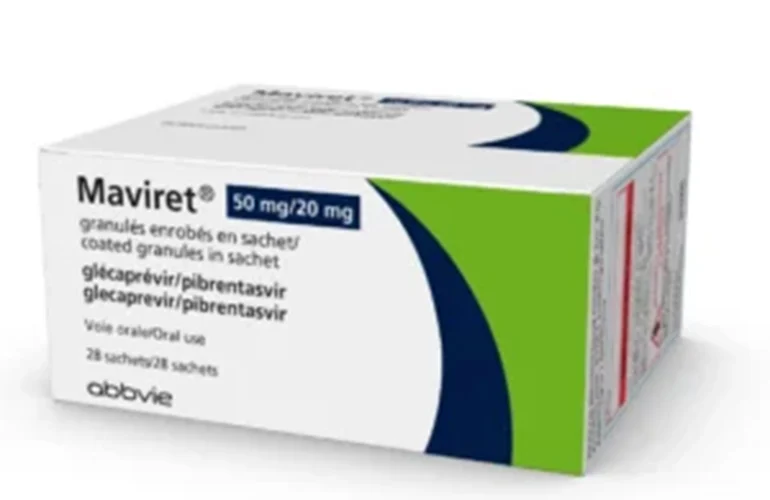
The landscape of hepatitis C (HCV) management has undergone a profound shift, yet a stark disconnect remains between clinical efficacy and public health outcomes. Despite the availability of highly effective oral direct-acting antivirals (DAAs) for over a decade, new infection rates in the United States have surged, with an estimated 69,000 Americans contracting the virus in 2023—a figure roughly double that of the mid-2010s. AbbVie’s Mavyret (marketed as Maviret in the European Union), a combination of the antivirals glecaprevir and pibrentasvir, stands at the center of this paradox. While clinical trials have demonstrated near-universal cure rates, the transition from controlled study environments to the complexities of real-world patient populations remains a significant hurdle in the global push to eliminate the disease.
A History of Clinical Advancement
The evolution of HCV treatment represents one of the most successful trajectories in modern pharmacology. Prior to the mid-1990s, options for patients were limited and largely ineffective. When the FDA approved the first alpha interferon injection in 1991, the treatment regimen was arduous, often accompanied by severe side effects and a viral eradication rate of approximately 10%.
The paradigm shifted dramatically with the advent of direct-acting antivirals. These therapies, which target specific non-structural proteins of the HCV virus to prevent replication, transformed a lifelong, often fatal, chronic condition into a manageable, curable disease. In 2017, the regulatory bodies in both the United States and the European Union cleared Mavyret for the treatment of chronic HCV across all major genotypes. The drug’s ability to achieve a sustained virologic response (SVR)—the gold standard for a cure—in as little as eight to 12 weeks established a new standard of care.
The Shift Toward Acute Intervention
In June 2025, the U.S. FDA granted a critical label expansion for Mavyret, authorizing its use as the first and only treatment for patients with acute hepatitis C. The European Commission followed suit in June 2026, approving Maviret for the same indication. This regulatory pivot addresses a long-standing clinical bottleneck: historically, many patients were required to wait for evidence of chronic infection before becoming eligible for treatment.
Clinical guidelines have long advocated for early intervention, yet administrative hurdles and insurance requirements frequently delayed access. By permitting the use of the medication during the acute phase, health authorities hope to intercept the virus before it progresses to chronic liver disease, cirrhosis, or hepatocellular carcinoma. As John Ward, director of the Coalition for Global Hepatitis Elimination, noted, the capability to cure patients early is an essential weapon in reducing the overall burden of the disease.
Trial Results vs. Clinical Reality
The Phase 3 trial underpinning the recent label expansion provided compelling data. Among the intention-to-treat population, Maviret demonstrated an SVR rate of 96.2% at 12 weeks. In the modified intention-to-treat population, which excluded non-virologic failures, the success rate reached 100%. Perhaps most significantly, there were no reported on-treatment virologic failures or post-treatment relapses within the study cohort.
However, researchers are now grappling with the fact that these results were achieved in a highly controlled setting. The trial population did not perfectly mirror the demographics most susceptible to the current rise in infections. For instance, only 14.3% of participants were classified as individuals who currently or recently injected drugs—a group that constitutes a significant portion of the new infection demographic. Furthermore, while nearly 50% of the participants were co-infected with HIV, all were already receiving antiretroviral therapy and were actively engaged with the healthcare system, which likely contributed to the study’s low dropout rate.
Addressing the Cycle of Reinfection
One of the most complex issues facing infectious disease specialists is the high rate of reinfection among high-risk groups. According to a systematic review of 36 studies, the reinfection rate among people who inject drugs is approximately 5.9 per 100 person-years, significantly higher than the 1.27 per 100 person-years observed in the general population.
The Phase 3 trial for Maviret included participants who had been treated for previous HCV infections, with some individuals having up to six prior infections. The results provided a degree of optimism: a history of prior infection, or even previous exposure to Maviret, did not diminish the drug’s effectiveness for the current episode. "The study found that a history of prior HCV infection did not appear to affect the SVR," said Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and a co-author of the trial. "These findings suggest that neither prior infection nor previous exposure to the same regimen compromised the virologic response."
Despite this, Dr. Gentile and other experts emphasize that medication alone cannot solve the crisis. Because antivirals do not alter the underlying risk factors—such as access to sterile injecting equipment or the prevalence of substance-use disorders—the drug must be integrated into a comprehensive public health framework.
The Path Toward Global Elimination
The implications of this, according to public health analysts, are that healthcare systems must move beyond a "test-and-treat" model and toward a "test, treat, and support" model. This involves:
- Harm-reduction services: Ensuring that those at high risk have access to safe equipment and addiction counseling.
- Rapid Retreatment: Establishing protocols that allow for immediate re-initiation of therapy in the event of a reinfection.
- Outreach Programs: Developing strategies to reach individuals who are marginally connected to the healthcare system, including those in housing-insecure or rural populations.
For providers, the recent approval for acute infection is a step toward removing administrative barriers. By eliminating the waiting period for chronicity, clinicians can now act on a diagnosis immediately. However, the true test of this therapeutic advancement lies in the ability of global health systems to deploy these treatments to the "hard-to-reach" populations that were underrepresented in the clinical trials.
Future Research and Strategic Needs
As the medical community looks toward the future, the focus must shift from pure pharmacological efficacy to "real-world effectiveness." This includes collecting granular data on the time elapsed between diagnosis and the first dose of medication, tracking loss-to-follow-up rates in marginalized populations, and documenting the success of retreatment strategies.
If the goal of eliminating hepatitis C as a public health threat is to be achieved, the medical community must recognize that reinfection is not a failure of the drug, but a signal that the patient is in need of more robust, multidisciplinary support. The success of Maviret in the laboratory is indisputable; its success in the clinic, however, remains dependent on the integration of pharmaceutical innovation with social, structural, and preventive healthcare efforts. As Dr. Gentile noted, those with repeated infections are among the most critical to engage, as their treatment offers the greatest potential for both individual health improvements and broader, population-level transmission reduction.