The regulatory landscape surrounding weight-loss medications has reached a critical juncture as the Food and Drug Administration (FDA) reports a surge in adverse event notifications linked to compounded versions of popular GLP-1 receptor agonists. As of May 31, 2026, federal data confirms 990 adverse event reports for compounded semaglutide and over 730 for compounded tirzepatide. These figures, while substantial, are widely viewed by public health experts as conservative estimates, given that many state-licensed pharmacies are not mandated to report such incidents to the federal government.
This data release arrives amid a period of intense scrutiny directed at the direct-to-consumer telehealth industry, which capitalized on the prolonged shortages of FDA-approved, brand-name drugs like Ozempic, Wegovy, and Mounjaro. While the pharmaceutical giants Novo Nordisk and Eli Lilly have largely resolved the supply chain constraints that triggered the compounding boom, a shadow industry of digital storefronts and affiliated pharmacy networks continues to operate, often utilizing aggressive marketing strategies and questionable clinical oversight.
A Chronology of the Compounding Boom and Regulatory Pushback
The rise of the compounded GLP-1 market is a direct byproduct of the unprecedented demand for metabolic health interventions that began in 2022. The FDA added Wegovy to its drug shortage list in March 2022, followed by Ozempic in August and tirzepatide in December. Under the Federal Food, Drug, and Cosmetic Act (FDCA), these listings created a temporary regulatory pathway for compounders to produce versions of drugs that would otherwise be protected by patents, provided they met specific quality standards.

By early 2025, however, the landscape began to shift. The FDA formally announced the resolution of the tirzepatide shortage in December 2024, followed by the semaglutide shortage in February 2025. This transition officially narrowed the legal window for compounding. The grace period for "enforcement discretion"—the period during which the agency allowed certain compounding practices to continue despite the availability of brand-name products—concluded on May 22, 2025.
In the months since, the FDA has moved to aggressively police the sector. February 2026 saw a wave of 30 warning letters issued to telehealth entities for illegal marketing, followed by another 25 in June. These enforcement actions cite concerns over misbranding, specifically regarding claims of equivalence to FDA-approved products, which the agency maintains have not been demonstrated in the laboratory or clinical setting for compounded variations.
The Anatomy of a Telehealth Network: The MEDVi Case
The business model of these compounding entities has drawn significant attention from both regulators and class-action litigators. MEDVi, a company that reportedly generated over $400 million in revenue in 2025 with projections reaching $1.8 billion for 2026, stands as a case study in the complexities of the current market.
In February 2026, the FDA issued a warning letter to MEDVi, alleging the company obscured the source of its drugs and falsely implied they were equivalent to brand-name products. While MEDVi management has publicly claimed the letter was directed at an affiliate, investigative records indicate that the company’s digital intake systems and terms of service linked patients directly to MEDVi LLC.
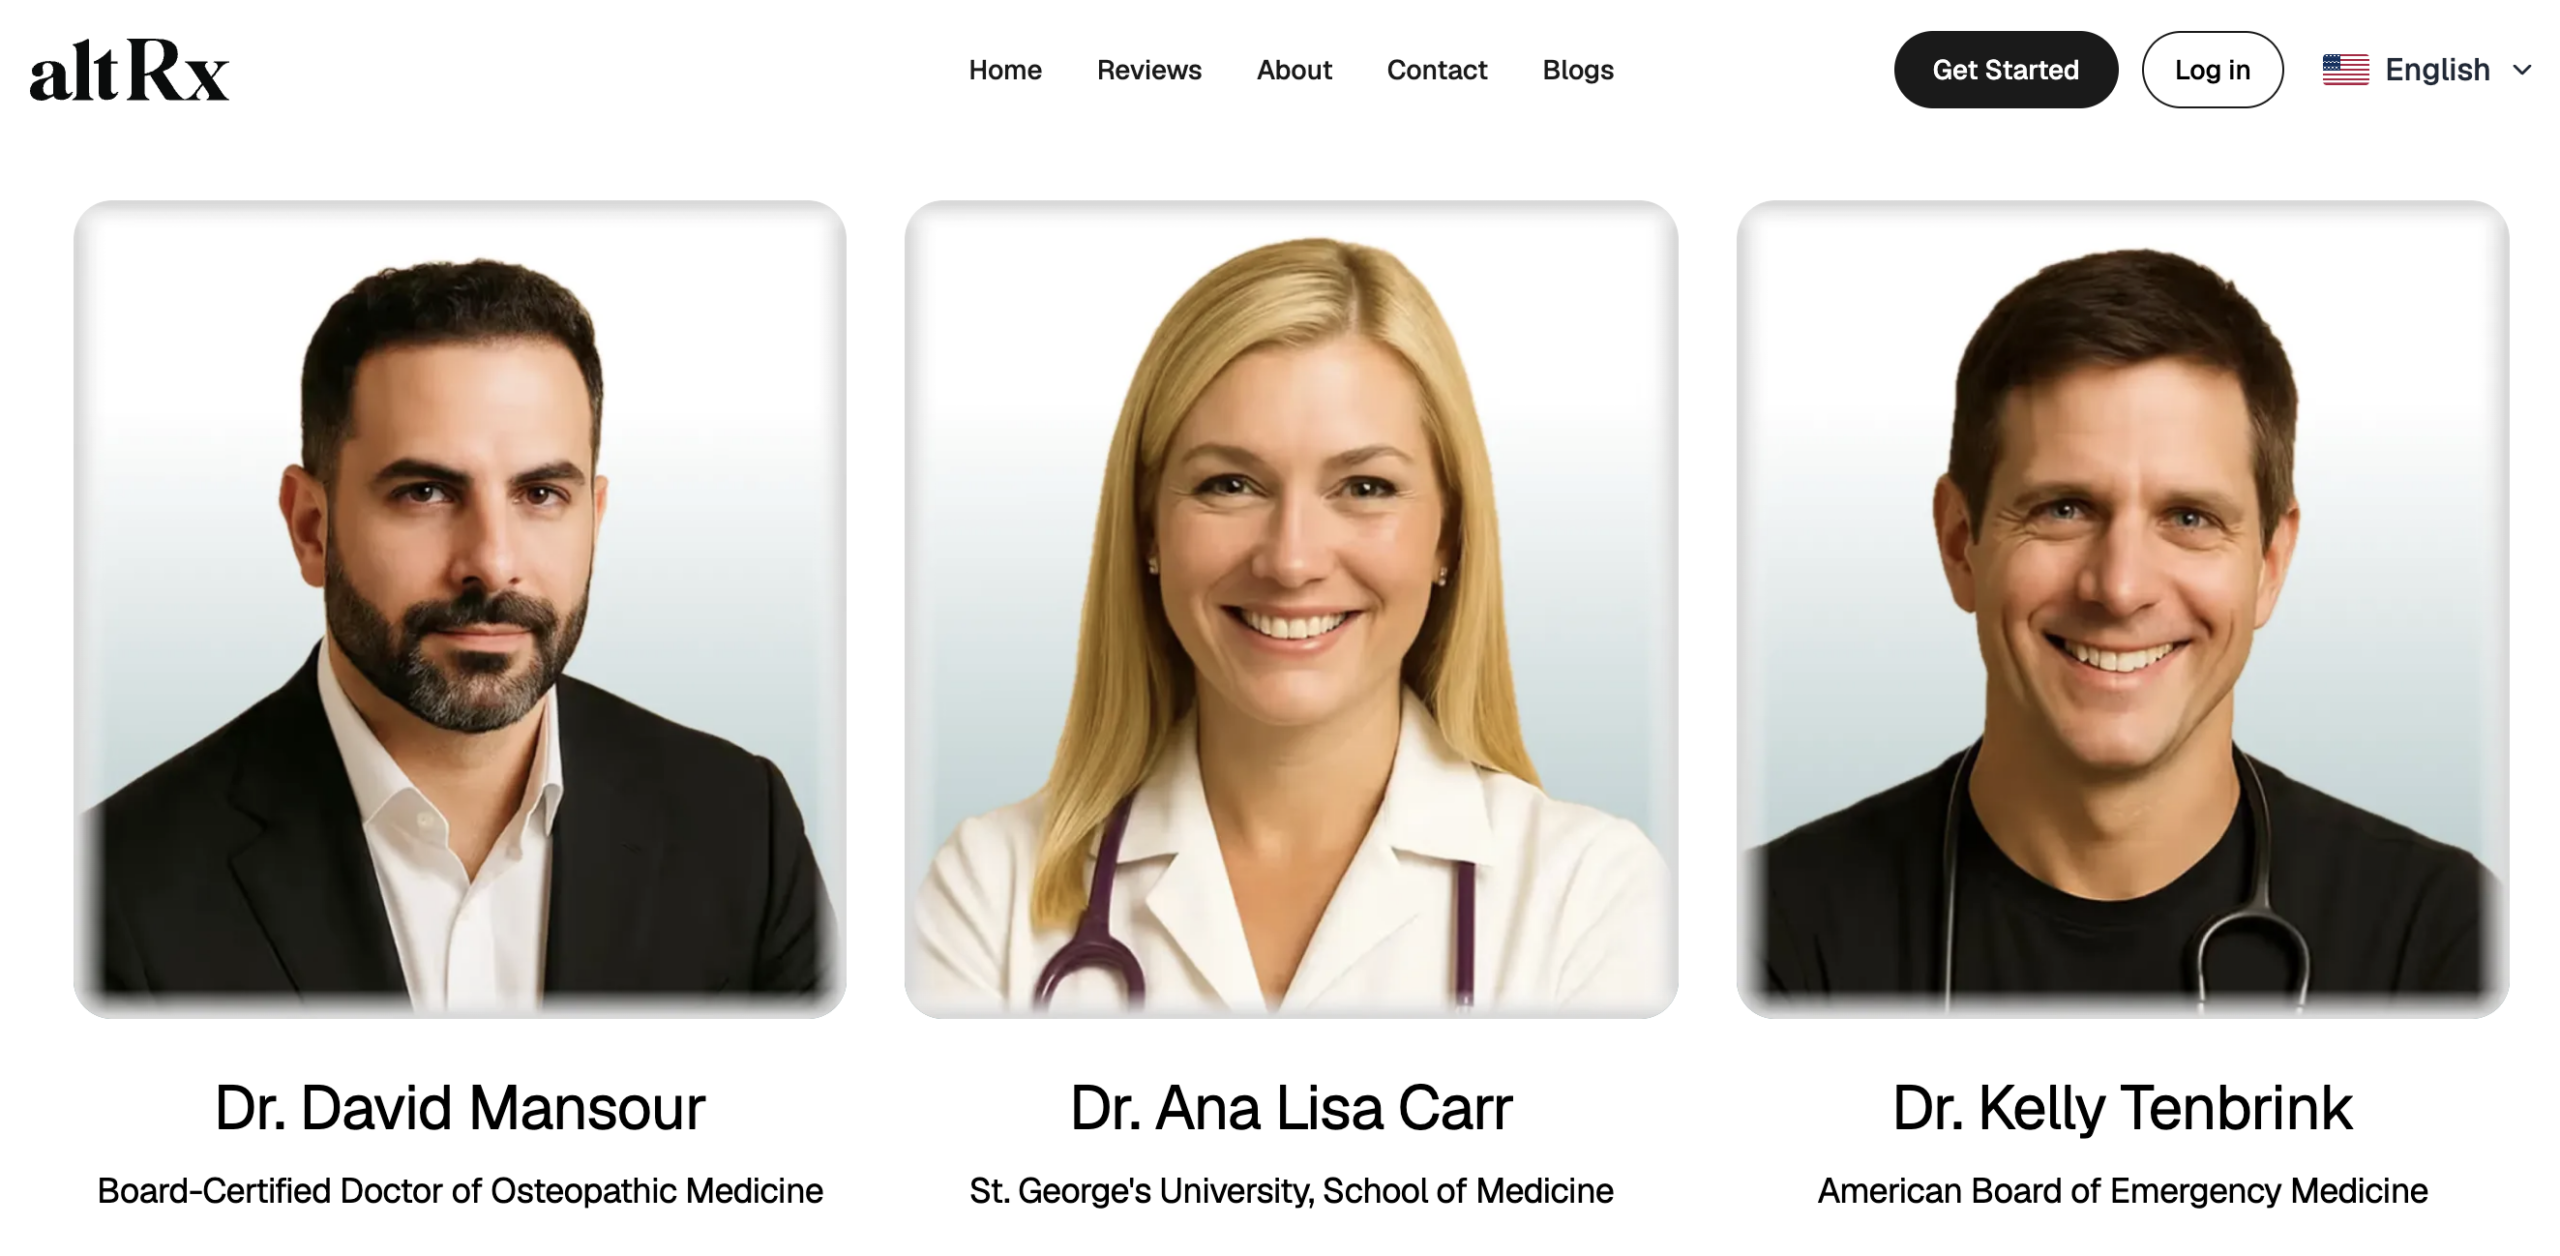
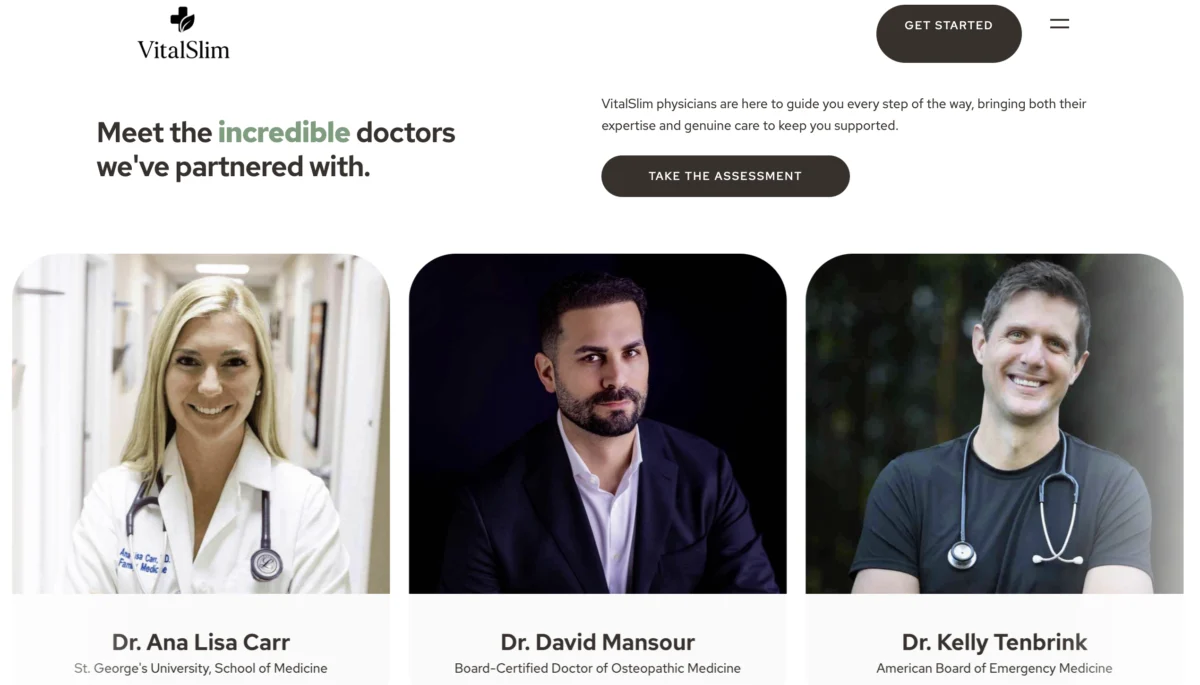
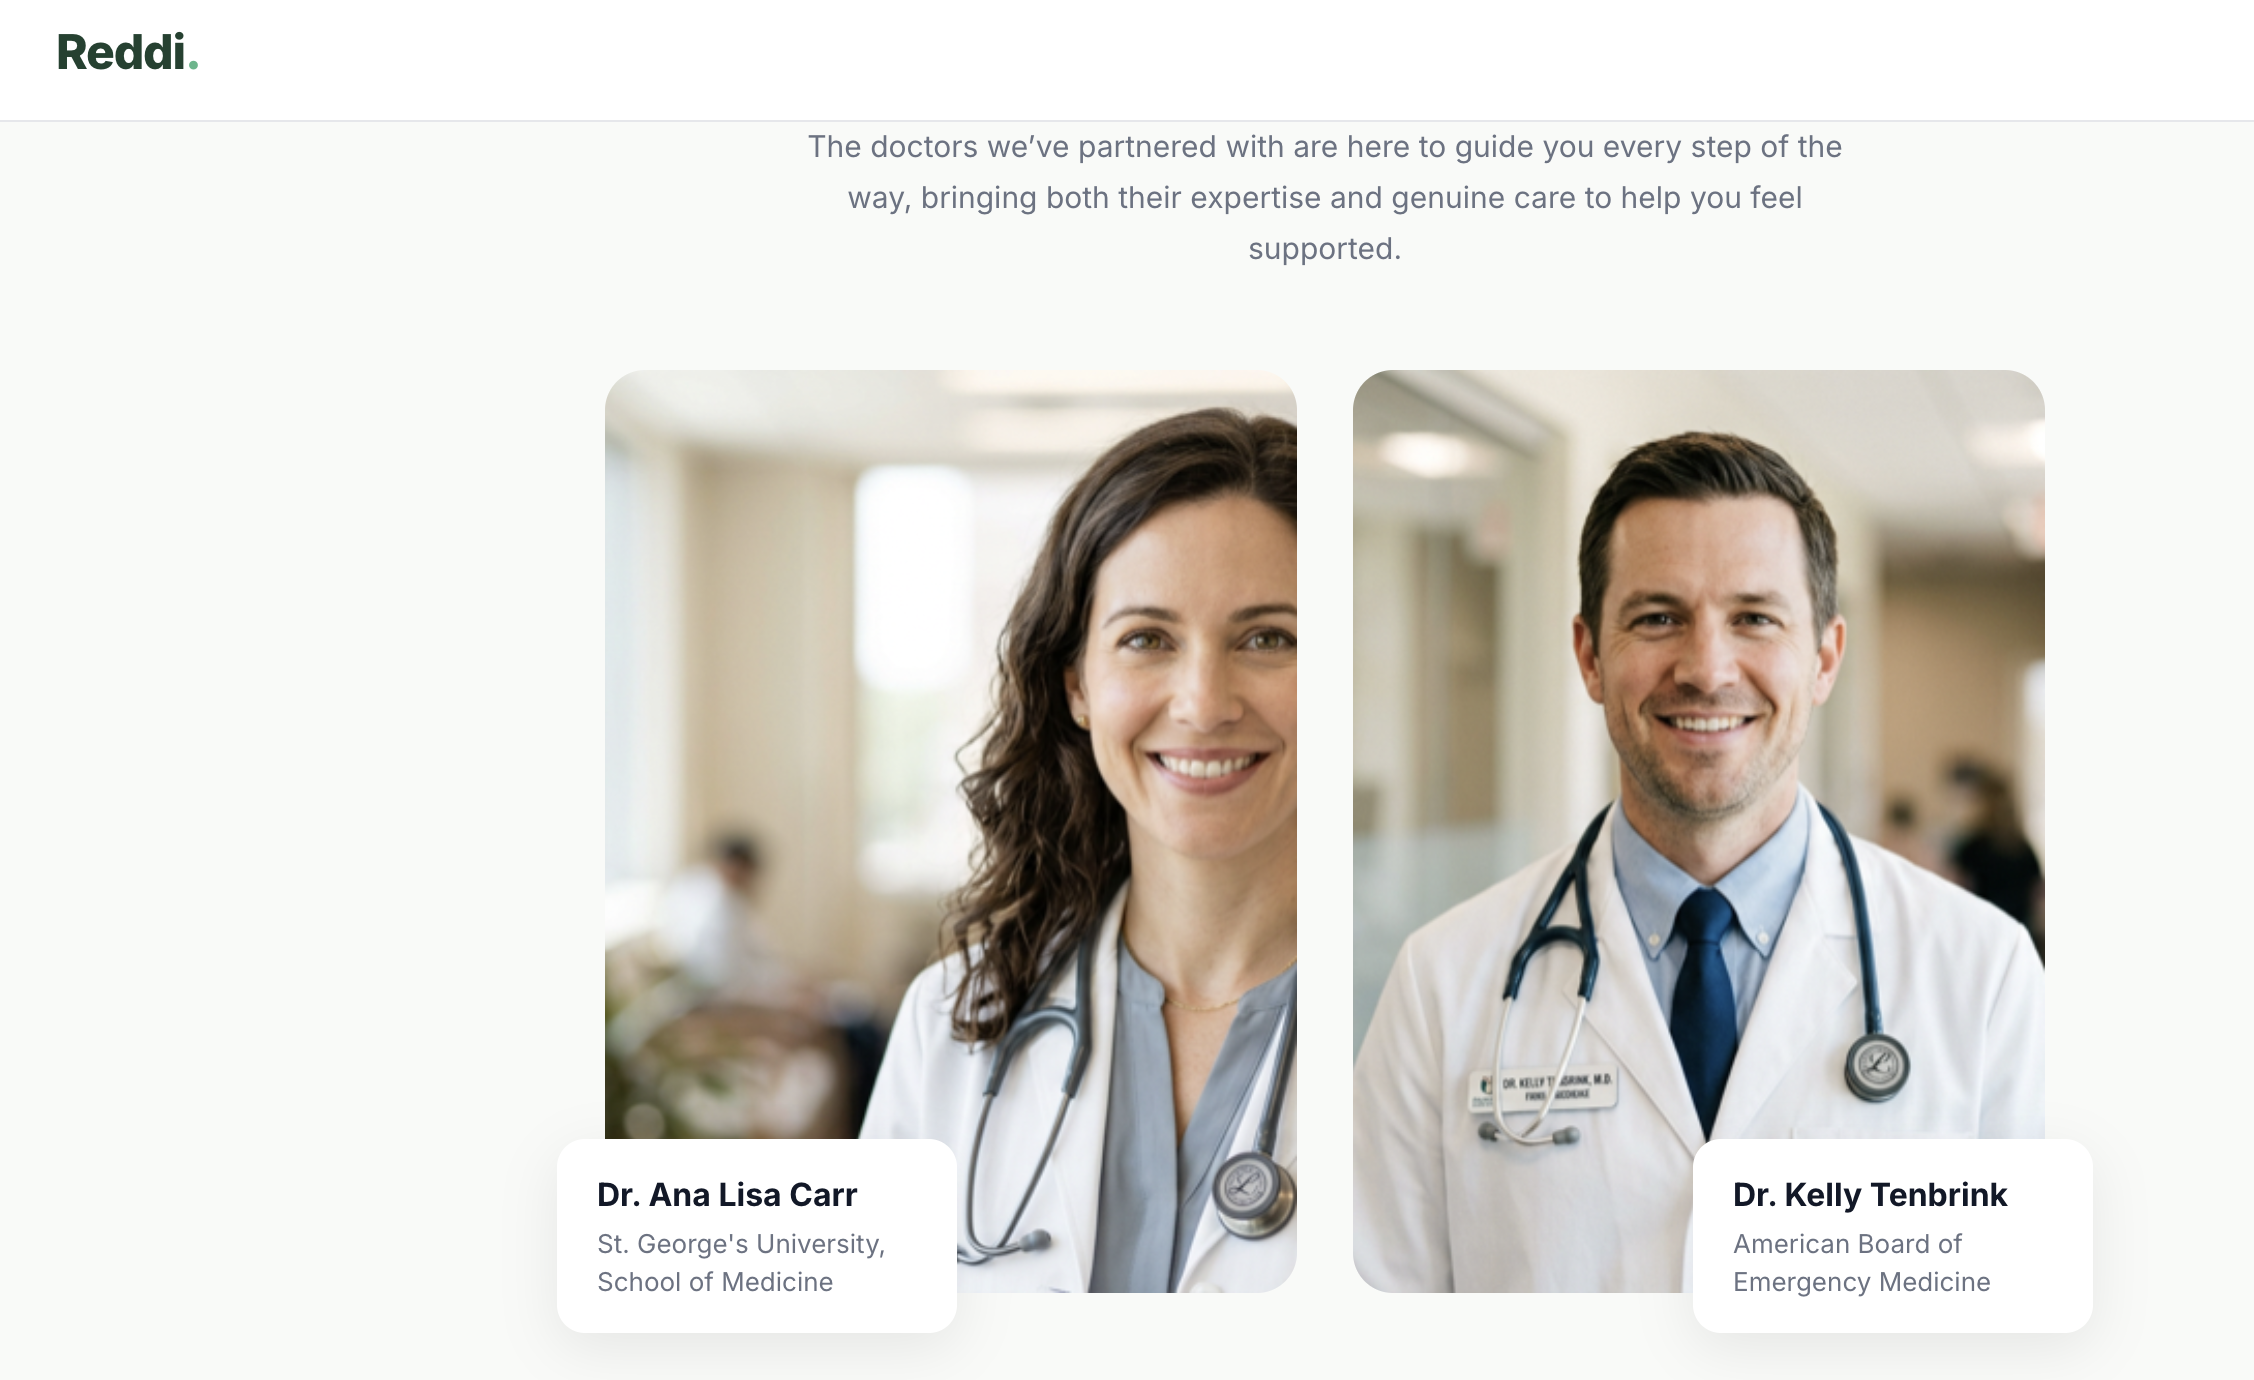
The operational strategy appears to rely on a standardized template: partnering with the same limited pool of telehealth clinician networks—such as OpenLoop Health—and relying on specific, often overlapping, pharmacy providers like Triad Rx. Recent investigations reveal that multiple competing telehealth sites, including VitalSlim and MDRxLabs, have featured identical medical staff, including Drs. David Mansour, Ana Lisa Carr, and Kelly Tenbrink. This pattern of shared personnel and infrastructure suggests a highly centralized "playbook" designed to maximize market penetration while insulating individual corporate entities from direct liability.
Public Health Risks and Clinical Implications
The safety concerns extend beyond mere regulatory non-compliance. America’s Poison Centers reported a staggering 1,500% increase in calls related to GLP-1 agonists between 2019 and 2025, totaling 22,966 cases. While a majority of these involve accidental therapeutic errors with approved medications, the compounded sector presents unique hazards.
Clinical experts have identified a recurring issue involving 10-fold dosing errors. Compounded products are often supplied in vials with instructions that differ from the pen-injector systems used by major manufacturers. Patients, confused by non-standardized syringe measurement units, have frequently administered doses far exceeding the prescribed therapeutic range. Furthermore, the emergence of oral tirzepatide offerings—a formulation not produced or endorsed by Eli Lilly—has sparked a civil RICO complaint. The lawsuit alleges that these oral products are marketed with no demonstrated efficacy or absorption, exposing consumers to financial exploitation and potential health risks.
Legislative Intervention and Industry Resistance
In response to the proliferation of these "essentially copies," the U.S. Congress introduced the bipartisan SAFE Drugs Act of 2025. The proposed legislation seeks to curb the abuse of section 503A of the FDCA by limiting the number of copies of a commercially available drug a pharmacy can produce to 20 units per month, unless a specific, medically necessary change is documented by a prescriber.
The industry’s reaction has been polarized. Organizations such as the Alliance for Pharmacy Compounding and the National Community Pharmacists Association (NCPA) have launched significant lobbying efforts against the bill. They argue that the 20-unit cap would unfairly penalize legitimate compounding pharmacies that serve patients with specific allergies or intolerance to the excipients found in mass-produced medications. Conversely, patient safety advocates argue that without these limitations, the "Wild West" of the GLP-1 market will continue to undermine the integrity of the U.S. pharmaceutical supply chain.
Pharmaceutical Industry Retaliation
Parallel to the federal enforcement, the manufacturers of the original GLP-1 drugs are pursuing their own legal remedies. Novo Nordisk has embarked on a multi-state litigation strategy, filing over 130 lawsuits and securing dozens of permanent injunctions against compounding pharmacies and telehealth platforms for patent infringement and trademark dilution. Eli Lilly has adopted a similar posture, targeting both the pharmacies and the digital intermediaries that facilitate the sale of unauthorized formulations.
These lawsuits, combined with the FDA’s recent crackdown, suggest that the era of unfettered access to compounded weight-loss drugs is coming to an end. However, the sheer scale of the market—estimated by some banking analysts to reach $1 billion in annual revenue—ensures that the transition will be slow and likely marked by continued legal volatility.
Broader Implications for Healthcare Delivery
The "compounding boom" has exposed critical vulnerabilities in the intersection of digital health and pharmaceutical regulation. The ease with which these companies were able to scale their operations highlights a gap in oversight regarding how telehealth platforms qualify and verify the medical necessity of prescriptions.
As the FDA continues to monitor the situation, the focus has shifted toward transparency. The agency’s insistence that patients verify the credentials of their providers and the source of their medication is becoming the primary defense against potential harm. For the thousands of patients who remain on these medications, the path forward remains uncertain. With the closure of the last enforcement discretion window and the potential for federal legislative action, the industry is entering a phase of consolidation and forced compliance.
The impact of this saga on future healthcare delivery will be long-lasting. It has ignited a national debate on the balance between access to life-changing treatments and the necessity of rigorous, centralized safety protocols. As the dust settles on the rapid expansion of 2025 and 2026, the pharmaceutical sector, regulators, and providers are left to reconcile the rapid growth of this market with the fundamental requirements of patient safety and clinical evidence. Whether the current measures are sufficient to contain the risks associated with the compounded GLP-1 market remains a primary concern for public health officials as they look toward the next chapter of metabolic medicine.