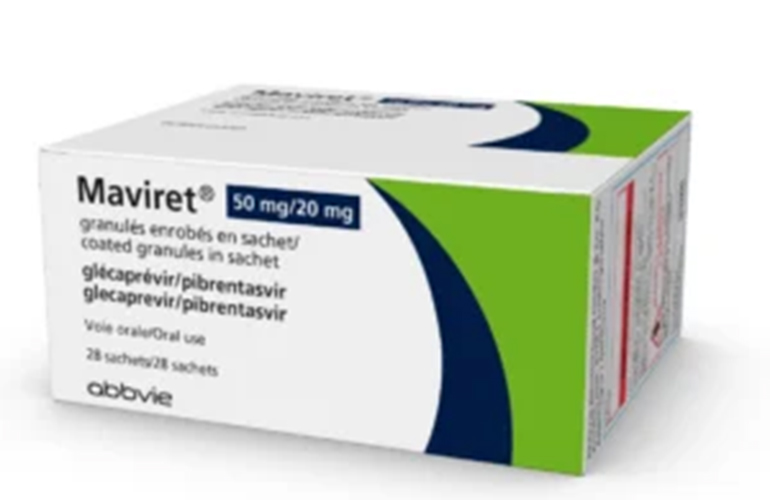
The global landscape of hepatitis C virus (HCV) management has shifted significantly in the past decade, moving from a era of difficult, often ineffective therapies to one where direct-acting antivirals (DAAs) offer a near-certain cure. Despite this, the public health burden remains acute. In the United States alone, an estimated 69,000 new HCV infections were reported in 2023, a figure that represents a doubling of incidence rates compared to the mid-2010s. This resurgence persists despite the availability of oral, short-course antiviral treatments that can eradicate the virus in eight to 12 weeks. AbbVie’s MAVYRET (glecaprevir and pibrentasvir), a cornerstone of this therapeutic class, reached a critical milestone in June 2025 when the U.S. Food and Drug Administration (FDA) approved its use for acute HCV infection. This was followed by a similar authorization from the European Commission in June 2026 for the drug, marketed as MAVIRET in the EU.
A Chronology of HCV Therapeutic Advancement
The evolution of HCV treatment is a testament to the rapid pace of modern pharmacology. Before the advent of DAAs, the primary treatment regimen relied on alpha interferon injections—a grueling process that spanned nearly a year, carried significant side effects, and resulted in a viral eradication rate of only about 10%. Since the early 1990s, when interferon was the standard of care, efficacy rates have increased by nearly an order of magnitude.
The regulatory trajectory for MAVYRET began in 2017, when the EU and the FDA granted approval for the treatment of chronic HCV across all major genotypes (GT 1-6). For years, clinicians were constrained by labels that prioritized patients with established chronic disease. The 2025 FDA label expansion, and the subsequent 2026 EU approval, represented a shift in clinical strategy: treating the infection while it is still acute. This paradigm shift aims to break the chain of transmission before the disease can progress to cirrhosis or hepatocellular carcinoma, and before it can be passed on to others.
Clinical Efficacy and the Question of Recurrence
The Phase 3 clinical data supporting the use of MAVYRET in acute infection demonstrate remarkable potency. In the trial population, the sustained virologic response (SVR) rate at 12 weeks reached 96.2% in the intention-to-treat analysis. Among the modified intention-to-treat population—which excluded non-virologic failures—the cure rate was 100%. Perhaps most compellingly, the trial recorded no on-treatment virologic failures or post-treatment relapses.
These statistics take on added significance when considering the study’s participant profile. Approximately 18% of those enrolled were undergoing treatment for at least their second HCV infection, and nearly 40% of that subset had two or more prior infections. In two cases, participants were being treated for their sixth infection. Crucially, the data suggests that prior exposure to MAVYRET does not diminish its effectiveness in subsequent infections. According to Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and a co-author of the study, the history of prior infection had no negative impact on the SVR, nor was there any emergence of drug-resistant viral strains that hampered follow-up success.
The Disconnect Between Trials and Real-World Implementation
While the clinical data are robust, experts caution that translating these results to the "real world" remains a complex challenge. Clinical trials typically involve highly monitored populations with strong links to the healthcare system. In the MAVYRET trial, for instance, nearly 50% of participants were people living with HIV who were already on antiretroviral therapy and, consequently, highly engaged with medical providers. Conversely, only 14.3% of the trial participants were identified as people who currently or recently injected drugs—a group that represents a significant portion of new HCV transmissions.
The disparity in engagement is critical. Data from a systematic review of 36 studies, covering over 6,000 person-years of observation, identified an HCV reinfection rate of 5.9 per 100 person-years among people who inject drugs. This is substantially higher than the 1.27 per 100 person-years observed in the general population. The implication is that even the most effective antiviral drug cannot function as a preventative tool if the underlying social and behavioral drivers of transmission are not addressed.
The Need for Integrated Care Models
Public health advocates and infectious disease experts are increasingly arguing that clinical success must be paired with structural support. John Ward, director of the Coalition for Global Hepatitis Elimination, has emphasized that treating patients early is the most effective way to prevent the escalation to chronic disease. However, "early treatment" requires a healthcare infrastructure that can identify acute infections rapidly and initiate therapy without administrative delays.
Historically, administrative barriers—such as requirements to confirm chronicity or navigate complex insurance prior-authorization processes—have forced patients to wait, often leading to disengagement from care. The new acute indication for MAVYRET is intended to mitigate these delays. By allowing clinicians to prescribe the medication immediately upon diagnosis of an acute infection, the regulatory change removes a layer of clinical bureaucracy.
However, Dr. Gentile notes that the strategy must go beyond the pill. Effective elimination requires a broader prevention framework that integrates harm-reduction services, such as access to sterile injecting equipment, treatment for substance-use disorders, and consistent sexual-health interventions. Furthermore, there is a necessity for robust systems of regular HCV RNA testing, particularly for those at high risk of reinfection. In this context, reinfection should not be perceived as a failure of the medication, but rather as an indicator that the current patient-support model is insufficient.
Implications for Future Public Health Policy
The challenge moving forward is to collect better data on populations that are typically excluded from traditional clinical trials. As the medical community looks toward the World Health Organization’s goal of eliminating viral hepatitis as a public health threat by 2030, the focus must shift to "hard-to-reach" populations. Future research, according to experts, should prioritize metrics that track the full spectrum of the care cascade: the proportion of diagnosed individuals who actually initiate treatment, the time elapsed between diagnosis and the first dose, the rates of loss to follow-up, and the effectiveness of rapid retreatment protocols following reinfection.
From an elimination perspective, the most vulnerable populations—those who have had multiple infections—may paradoxically be the most important for public health outcomes. Treating these individuals quickly not only provides personal health benefits but also significantly lowers the viral reservoir within a community, thereby reducing the probability of new transmission events.
The approval of MAVYRET for acute infection is a significant, albeit singular, component of a larger strategy. While the drug itself is highly effective, the path to ending the HCV epidemic in the United States and abroad remains dependent on addressing the logistical, social, and economic barriers that prevent the most at-risk individuals from accessing the care they need. The shift from "treating chronic illness" to "preventing the progression of acute infection" is a promising start, but the success of this strategy will ultimately be measured not by the 96% success rate in a controlled trial, but by the ability of public health systems to deliver that same level of care to those standing outside the traditional healthcare system.
As the medical field moves into the latter half of the decade, the focus remains on closing the gap between the efficacy of available antivirals and the real-world effectiveness of public health interventions. Without such integration, the rising tide of HCV infections may continue to outpace the technological advancements designed to suppress them. The lessons learned from the recent MAVYRET trials underscore a fundamental reality: while biotechnology has provided the "cure," the "elimination" of the disease remains a social and systemic endeavor.