In the global effort to eradicate hepatitis C (HCV), clinical success has frequently collided with the sobering realities of public health accessibility. While recent regulatory milestones have positioned AbbVie’s direct-acting antiviral (DAA) therapy, Maviret (known as Mavyret in the United States), as a potent tool for treating acute infections, the medical community remains cautious about the translation of trial-setting efficacy into real-world effectiveness. With approximately 69,000 new HCV infections reported in the United States in 2023—a figure that has roughly doubled since the mid-2010s—the urgency for streamlined, accessible treatment has never been higher.
A Chronology of Clinical Advancement
The journey toward a simplified treatment protocol for HCV has spanned over three decades. When the FDA first approved alpha interferon injections in 1991, the landscape of HCV care was bleak, with viral eradication rates hovering at a mere 10%. The subsequent decades saw iterative improvements, but the advent of direct-acting antivirals, which target the virus’s replication cycle directly, fundamentally altered the prognosis for infected patients.
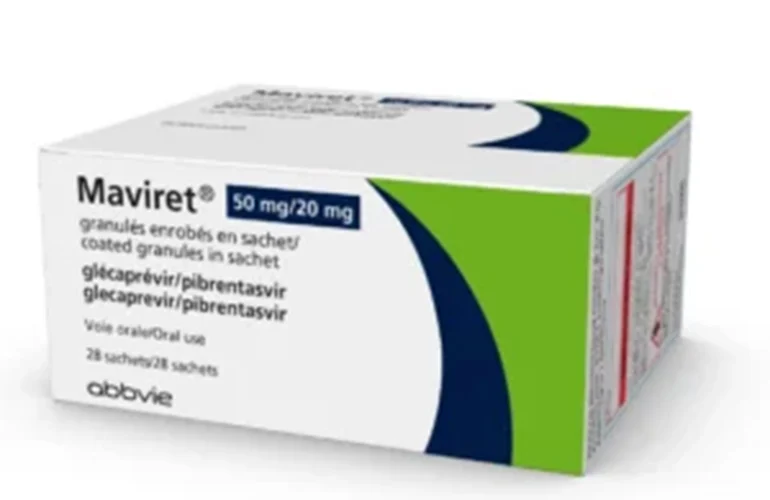
AbbVie’s Maviret, a combination of the antivirals glecaprevir and pibrentasvir, emerged as a landmark therapeutic. The drug received its initial approval for chronic HCV in the European Union in 2017, followed by an FDA green light just six days later. However, the label was initially restricted to chronic cases, often requiring clinicians to wait for evidence of persistent infection—a bureaucratic hurdle that frequently led to patient attrition.
The regulatory landscape shifted significantly in 2025 and 2026. In June 2025, the FDA granted an expanded indication for Mavyret to include acute hepatitis C, making it the first and only oral antiviral cleared for such use in the U.S. The European Commission followed suit in June 2026, approving the same label expansion for Maviret. This regulatory pivot was designed to allow providers to treat patients immediately upon diagnosis, theoretically closing the window of transmission and preventing the progression to chronic liver disease.
Efficacy Data and the Persistence of the Virus
The clinical trials supporting these approvals showcased a high level of efficacy. In a Phase 3 study, Maviret demonstrated a sustained virologic response (SVR) rate of 96.2% at 12 weeks in the intention-to-treat population. Notably, the study recorded a 100% response rate in the modified intention-to-treat population, which excludes non-virologic failures. Perhaps most impressively, researchers observed no on-treatment virologic failures or post-treatment relapses among the cohort.
The trial data also addressed concerns regarding patients with prior exposure to the virus. Approximately 18% of the study participants were being treated for at least their second HCV infection, with some having as many as six prior instances of the disease. Crucially, the presence of a history of HCV infection—or even prior treatment with Maviret itself—did not diminish the efficacy of the regimen. These findings provide a robust clinical basis for the argument that reinfection should be treated as a routine clinical event rather than a barrier to future care.
The Challenge of the "Real World"
Despite these impressive numbers, experts emphasize that the controlled environment of a clinical trial rarely mirrors the complex social determinants of health that characterize the actual patient population. Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and a co-author of the recent trials, notes that while the drug is biologically effective, its impact on the epidemic depends entirely on reaching those at the highest risk of transmission.
The demographic makeup of the trial population highlights these gaps. In the Phase 3 study, only 14.3% of participants were classified as current or recent people who inject drugs (PWID), a demographic that faces significant barriers to continuous healthcare. Furthermore, while nearly 50% of the participants were co-infected with HIV, all were already receiving antiretroviral therapy and were, by definition, tethered to the healthcare system.
"This study provides strong evidence of antiviral efficacy, but it does not fully answer the question of effectiveness in populations that are least engaged in care," Dr. Gentile explained. For individuals experiencing housing instability, substance use disorders, or lack of insurance, the administrative process of getting a prescription and adhering to an eight- to 12-week regimen can be insurmountable.
Integrating Treatment with Prevention
The disparity between controlled clinical outcomes and public health statistics is stark. A systematic review of 36 studies found that the reinfection rate among people with recent drug use is approximately 5.9 per 100 person-years, significantly higher than the 1.27 per 100 person-years seen in the general population.
This leads to a fundamental question: Can the drug solve the epidemic, or is it merely a component of a much larger strategy? John Ward, director of the Coalition for Global Hepatitis Elimination, has consistently argued that providers can cure virtually all patients before the disease becomes chronic, provided they can reach them early. However, as Dr. Gentile points out, antiviral treatment does not modify the underlying risk factors.
"Repeated treatment must be integrated into a broader prevention strategy, including harm-reduction services, access to sterile injecting equipment, treatment for substance-use disorders when appropriate, sexual-health interventions, regular HCV RNA testing, and rapid retreatment following reinfection," says Gentile.
Implications for Future Policy and Care
The expansion of the Maviret label to include acute infections serves as a necessary, if not sufficient, component of the global elimination strategy. By removing the requirement to confirm "chronicity," the FDA and the European Commission have effectively lowered the barrier to entry. Clinicians no longer need to navigate the administrative "wait-and-see" approach that previously allowed the virus to spread unchecked within communities.
Looking forward, the medical community is calling for more granular data. To successfully curb the rising rates of HCV, research must move beyond SVR percentages. Future studies need to capture metrics such as the "time to first dose" after diagnosis, the proportion of diagnosed patients who successfully initiate treatment, and the frequency of successful retreatment following a reinfection.
Furthermore, the focus must shift toward "de-medicalizing" the treatment process. This could involve point-of-care testing in non-traditional settings, such as community centers, mobile clinics, and harm-reduction sites, rather than traditional hospital-based hepatology clinics.
Conclusion
AbbVie’s Maviret has proven that the biological tools to eliminate hepatitis C are firmly in our hands. With a 96% cure rate, the challenge is no longer the potency of the medicine, but the resilience of the delivery system. The recent label expansions are a tacit acknowledgment that the traditional model of care is insufficient for the current epidemiological crisis.
As policymakers and healthcare providers look toward the future, the goal is to shift the narrative around reinfection. Rather than viewing a second or third infection as a failure of the patient or the drug, it must be viewed as a signal that the healthcare system needs to be more agile. If the goal of global HCV elimination is to be realized, the integration of rapid treatment into the existing fabric of harm-reduction and primary care is the next essential frontier. The success of the drug is certain; the success of the public health response remains a work in progress.